Sunday, January 3, 2021

Swallowing at the crossroads

Speech - language pathologists (SLP's) are being engulfed in an identity crisis, within the community of healthcare providers. Among primary care physicians, medical speech-language pathology services are often an afterthought. Given the history of confusion over the name of its practitioners, it is confusing to their stakeholders that SLP's in healthcare now get the majority of their work from swallowing referrals. There are also concerns about the burnout rate among SLP's; the relatively flat salary schedule for healthcare clinicians; requirements by employers that their clinicians are ALWAYS available; the need to justify your existence with continually high productivity; - but there is also hope for the healthcare SLP who feels she/he is being compartmentalized as a "swallowing technician".... I actually was called that once by an internal medicine resident....mortifying, to say the least, when medical SLP's have to know how swallowing works in its complexity, and we must know how to work with people who need swallowing help. Doctors. What a mess they can make.



The medical SLP who dives into each day of swallowing problems, will swim toward an intersection of known scientific - cultural - political phenomena, that will be significantly addressed by the involvement of SLP clinicians. Sea changes in social science, in health, in politics and in culture will also serve the personal and professional growth of SLP practitioners, as we confront their effects on the field. Let's briefly identify a few of the intersecting forces, with potential to affect clinical practice patterns.


 1. Dysphagia management: there is a realization that, even though the technology exists to provide modified diets, safe to swallow by persons with diagnosed dysphagia - the consumer may not want to eat the diet! Practice trends exist that allow the consumer and her supports to train for swallowing a 'normal' diet,  through use of compensatory strategies.  With this approach, a modified diet should be considered a temporary intervention in the majority of dysphagia management cases. "I can eat my favorite food, when I ____", is the outcome desired, not "I can eat my favorite food, when it is prepared by ____". When you can offer your consumer potential to consume their preferred diet, they will often work hard for you - for THEIR goals.

 2. Food viscosity: When you change the viscosity of a material, you affect its ability to flow through a conduit. A consumer of SLP services,  who wishes to improve her swallowing of favorite foods, will have viscosity as one powerful tool. Can you chew and manipulate a pretzel bun to the consistency of oatmeal, through your mouth to TRIGGER the swallow in your throat? Do you swallow the ginger ale right out of the bottle, or does it need more mass to be easily felt and controlled past your airway? Dedicated viscosity modifications, the product of modern science, are easier than ever to find in pharmacies and big box stores. Can any more natural change agents do the same? Clinical experience says YES. Talk with your clinician for details. When you can augment the foods your consumer likes, so she can eat/drink them, they will often try their best.


3. Cooking: making not only the food easy to swallow for persons with dysphagia,  but also tasty, convenient and palatable, is the mission of the family, the cooks, the servers, and the activated patient who prepares the consumer's diet. Is it served as it was intended, or is it cold? Will flavors and seasonings enhance the taste, and the enjoyment of the food and drink? Are salt, fat, acid and heat appropriately utilized to make this, the best meal your consumer has had recently? Does the place where the consumer is eating, help focusing on swallowing better? Are drinking vessels, utensils, condiments easily used? If an SLP and the consumer's supports can tailor the meal to the consumer's changing needs, then you might have the therapeutic alliance you want. The patient can eat for pleasure, while consuming an appropriately safe diet. 

 4. Urban farming/community gardening: giving the SLP consumer food and drink she/he wants to eat, might include making available locally grown, fresh and nutritionally dense food. Both urban farms and community gardens can provide seasonal fruits and vegetables, which when grown organically and harvested timely, can heighten the experience of eating a least restrictive diet. A consumer that enjoys easily eaten food, grown cleanly and locally, may even want to grow some of her/his own food. When a consumer and her supports gets involved in bringing the food to their table, savoring it can make it easier to swallow.

5. Locavore: the person who eats like a locavore, regards the food grown locally and available only in season. 


There may not be an immediate connection between an SLP consumer's dietary plan, and the decision to eat only locally produced food. Yet the consumer who consumes only locally grown food, helps change dependence of a food community on a global food supply chain. When you want to have a supply of a seasonal food throughout the year, you rely on traditional food preservation methods, eg canning or drying, to keep available longer, the food you want to eat. A local food consumer has a closer connection to the environments where food is grown, and where it is consumed. When you can eat seasonally, locally, cleanly, you have the best of all possible foods.

 6. Culinary medicine: Approximately thirty clinical training programs around the world help physicians learn to properly prescribe food as a treatment for medical problems. Liaisons with nutritionists, chefs, dieticians, food scientists, food industry representatives,  consumer groups and others may aid your family doctor, to guide you to the best dietary solutions for your health.  Will your doctor give you samples (amuse bouche) in the office? Does the industrial food industry throw lots of money at physicians, with the goal of delivering cheap, mass marketed and convenient-to-produce food, to consumers?? When your primary care physician has access to food as medicine, you have available a medicine with centuries of proven effectiveness.

7. Food insecurity: Communities of all cultural, ethnic and economic stripes do not have adequate access to healthy food for many of its citizens. The roots of food insecurity may lie partially with limited personal income, with limited public support for food support programs and limited perspectives by the public, about the persons seeking food security assistance. Helping our food - insecure families, neighbors and communities get those resources to feed themselves, can be a rising tide that raises all boats. Food insecurity, hunger, poverty, chronic disease, economic stagnation, educational ceilings, and political instability: each are a pressure wave pushing against the stability of the culture. When food markets find their way into "insecure" neighborhoods, so that people of all levels of society have equal access to good food, we have a healthier society.



8. Environmental justice: a community resident inhales polluted air, or ingests food or drink contaminated with toxic material that endangers generations of residents. The toxic material often has an industrial source,  placed in close proximity to residential areas when residents had little political power to keep the industry out. Industrial byproducts e.g. coal ash, heavy metals, and corrosive solvents accumulate in the industrial site - challenging the quality of life frmor residential sites. Industries have little incentive to clean up their byproducts, for civic leaders do not wish to alienate the generators of tax revenue and payroll for their jurisdictions. The cumulative effects of exposure to toxins for community residents, will often lead to chronic disease, if not severe afflictions that are atypical for the disease prevalence. 

9. Climate change: It is a long - kindling inferno. No matter its presentation, the warming of our climates degrades our ability to grow food. Limits on water access yields limited ability to raise plants and livestock. The ecology that supports food production loses its equilibrium. Limited food production opens a Pandora's Box of stress on food and financial markets. Societies having difficulty feeding themselves will fight to control resources. When persons can't find food for themselves and their families, they will do what is necessary to survive. As data from NOAA illustrates, average annual world temperature has grown logarithmically since 1980. How much more time do we need to achieve climate justice?


10. Forest bathing: in Japan, where the practice originated, it's called 'shinrin-yoku'. A forest bather spends time in nature for  refocusing, reflection and healing. Turn off and set aside your technology, when you forest bathe. You ultimately discover that the experience can be created, out of the forest. It's possible, even in your garden. 

11. DoHD: The Developmental Origins of Health and Disease hypothesis suggests that critical periods, cumulative disadvantage, chains of risk and accumulation of social determinants can constitute an approach to effective management of health risk through the life span.

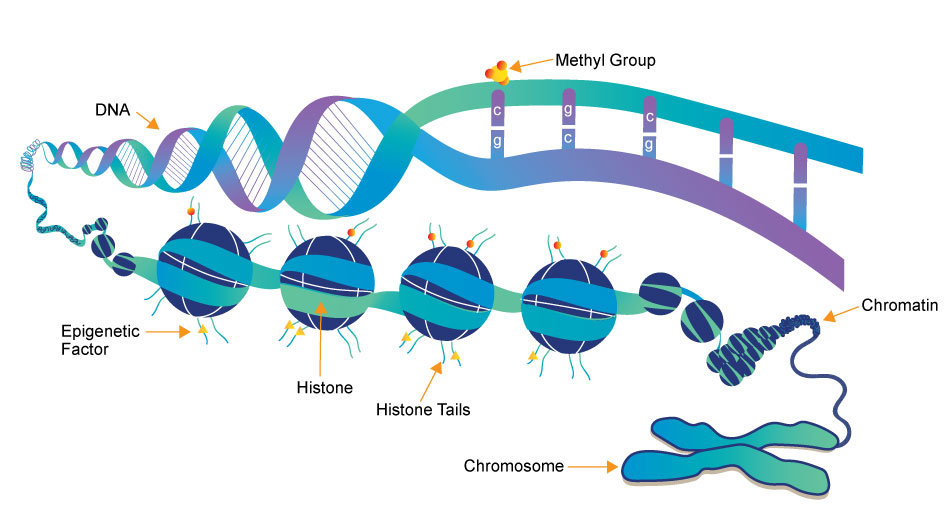
12. Epigenetics: social and environmental influences on health have been reflected as changes in the structure of chromosomes. Not only will your grandparents' behaviors have influenced your own health, but your health status will be reflected in the genetic potential of your descendants. 


13. Life Participation Approach: in spite of significant impairments to function, including breakdowns of independent feeding and swallowing, consumers of SLP services can be helped to eat some of the foods they want. Making it possible to safely/efficiently swallow foods, might keep the consumer participating in the social network. 

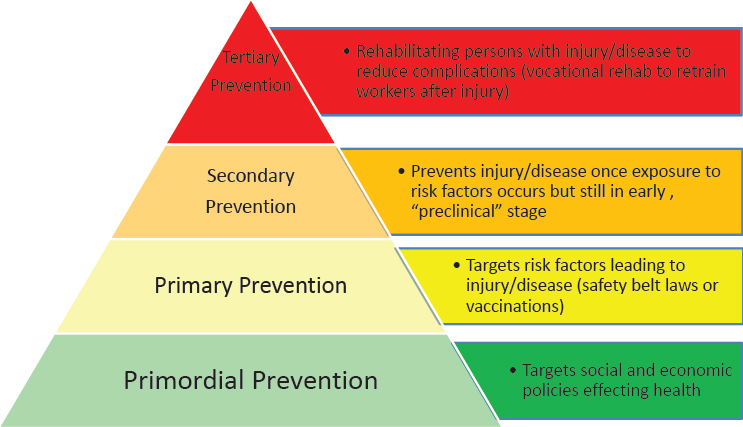
14. Primary vs. Primordial prevention: SLP clinicians who have become accustomed to prevention at the secondary level (identifying persons with impairments), will now find prevention can occur at primordial (prevention of risk factors for disease) or primary (modification of the risk factors) levels. If the SLP clinician wants to augment a clinical practice with prevention activities, e.g. assisting a consumer in improving the quality of food eaten, that clinician has a larger world in which to work. The big world will be much more conscious of what SLP does. 


Friday, January 1, 2021

What do I know about cardiovascular disease?


Happy New Year, blog readers! We are all ready for a fresh start in 2021, and this posting reflects my need to start towards a new horizon for my CSD work. 

You'll find below a link to a second survey, that wants to find out how much you know about cardiovascular disease (CVD), what causes it, and how its impact can include the onset of speech, language, cognitive and swallowing disorders. I hope you find the survey interesting, and that it might whet your appetite to learn more about CVD, and how prevention efforts against it must start as early as possible for your consumers. 

You'll find the survey at https://www.surveymonkey.com/r/TFT87DH

I hope you might complete the survey by 1/31/21. Thanks for your interest.


Wednesday, December 30, 2020

What I re - learned this year


Hustle? Yes, we SLP's have hustle in spades (hearts, clubs, and diamonds)! Whether squeezing in an improvised consumer visit, or an unexpected hard right turn to the daily schedule, we always have a higher gear.


Traveling among facilities I serve, there may be texts and emails to scan and process. Voice calls from consumers and their supports need answering. The therapy session for which you had prepared the BEST customized materials ever, need be replaced with a priority evaluation you discovered when arriving at your next stop. A family meeting for which you had mentally budgeted fifteen minutes, is now running past AN HOUR and fifteen minutes. The COVID - 19 mitigations are changing again, so an ad hoc training meeting is called. Hustle. 


Discipline? Pish tosh. People depend on us. We have great science, great methods and great history to keep us focused and propelled to reach the best outcomes possible. 

I think many of us would want to wear a patch that resembles the image above, if we have a standard work uniform like a scrub outfit. The medieval scribe toiled and squinted endless hours to get manuscripts copied. We squint, toil, copy and paste, curse at files lost that must be redone, and distill often detailed observations into rigid technical prose. It's what we do. It drives the healthcare and educational systems. It isn't what we aspired to do, when graduate training started. It's what we get flagellated for when it's not done well, and for which we flagellate our tablets, laptops, desktops and phones to get through the workday. It's what we do.

Power? We help people communicate, think and swallow better. As the slogan asks, what's your superpower? 

The more we do 'that voodoo that speech therapists do' (a manager actually told me that once), the more we realize and take to heart that our profession is one of civilizations great levelers; that even with the wide and deep reach the field now has, we have - all clinicians of all credentials,  in all settings - the wish to help all who have a need, to grow their quality of life throughout their lives. This is what we really do. 
 

Farewell to 2020, so fast, and all the best to my colleagues, their circles of support, and all people they support, all around the world!

Sunday, December 27, 2020

Can speech-language pathologists offer primary prevention of cardiovascular disease for consumers ?


Dear speech-language pathology colleagues, 

I hope the survey accompanying this post perks your interest in the science of chronic disease prevention. My goal for sharing the survey with you is to discover how many of us include prevention activities in our practices. 

* Do you help your consumers lessen or avoid risks for disability? 

* Do you participate in screenings that will help identify potential consumers of your services? 

* Do your evaluation and treatment sessions include lessons in health literacy, so that your consumers might continue to function at their best? 

You can access the survey by going to - https://www.surveymonkey.com/r/MQ7K658 

Please try to complete the survey by 1/15/2021, to help me understand how prevention is influencing our field. 

SOME EXPLANATORY NOTES:


Modifiable Risk Factors: fitness, nutrition,  weight control, smoking, environmental health, mental health, etc.

Non-modifiable Risk Factors: age, gender, ethnicity, family history, etc. 

Send any comments about the survey to me at payne.carey11@gmail.com. 

Thanks, 

Carey Payne, MCD, CCC-SLP
"Pretty Wonderful, Communication"  


Sunday, December 6, 2020

Favorite speech things: Christmas 2020

Patients, or clients; consumers, what have you - !

Speechies will strive to help you meet your goals, true. 

But at this time of year, we do excel

At getting more function, so you swallow well.....- you say - "Don't you help talking and thinking?

Aren't you called first a SPEECH THERAPIST?" - blinking - 

Yes, we do all that stuff all day and night; 

But it's in the swallow, we best make things right. 


When you celebrate at the Holidays

You want to nosh and quaff

And speechies will help you see through to the end

So eating and drinking, are good enough!


Try some desired food; sip a good beverage - 

You'll find out what skills will need careful leverage - 

Protect the airway, while increasing flow, 

You'll feel the wassail the best that you'll know!


When the plum pudding, crispy fresh latkes,

Or Hoppin' John make you smile; - 

Your happily swallowing holiday tastes

Will help close your holiday clinic file.  


Saturday, November 21, 2020

Credo Crudo

Since this blog was started in 2012, I've discovered that I can and do get lost in the forest of ideas I've published - 133 posts so far! Following is a list of principles that I have tried to follow with these blog entries. And, in the spirit of the post title, these ideas may seem rough and raw, but there's a lot of flavor in each position I've taken in posts. So, what does this blog believe? Please be patient with the bullet points. They can make a narrative choppy, but each concept is like a bite of the raw ingredient - equally yummy, and we hope you agree. Comments on these posts are always welcome. . 


* The communication sciences and disorders (CSD) professions, whether audiologist, teacher of the deaf, or speech-language pathologist, develop highly specialized practitioners who work in basic science and evidence - based practice; 

* College graduates take the jobs in CSD, yet they serve persons of all ages, educational and social levels, cultures and needs. The persons served deserve their needs to be met, as they see them. 

* Evidence - based practice (EBP) exists as an equilibrium of clinical knowledge, scientific evidence, and the expressed needs of persons served; 

* The three - legged stool of EBP is realistic about how CSD professionals make day - to - day decisions in their work.

* External scientific evidence (eg randomized controlled treatment trials) is held up as a gold standard of proof for effective clinical intervention; 

* The randomized controlled trials have not been done for some clinical interventions. Will you participate in such a study, or will less robust evidence suffice to guide your clinical work?

* Clinical knowledge and experience allow the therapeutic alliance of client and therapist, to craft an ideal plan for behavioral change; 

* Ask your consumer, "How will you know when you're better?", or "How will you know if what we do is working?". This perspective may help identify the discrete goals the consumer has in mind.

* The needs and wishes of persons served by CSD intervention should remain primary for the clinical practitioner; 

* Buy - in for the plan of care by the consumer, and by the circles of support,  helps the CSD professional offer a broad range of interventions to meet the goals identified;

* The CSD practitioner, through focus upon the goals that encompass a plan of care, helps persons served attain the best quality of life; 

* The CSD consumer builds a quality of life through high - quality services, that helps the consumer gain more control over life's outcomes;

* The quality of life for persons served by CSD professionals increases along with increased bodily function; 

* At times the CSD practitioner treats the impairment of persons served; at other times, treatment is at the level of activity; still other times require treatment of participation;  

This line of argument should lead you to think about the WHO International Classification of Function (ICF), which for me has been a major anchor for my clinical work over the past 20 years. 

More on that later! Let's leave you with another bite: 


Sunday, October 11, 2020

Your next shift starts soon

I just have one day off per week, and even then they can find me. THEY can find me....voice, text, Tweet, email, Facebook message, Zoom; one day I imagine they'll insist on FaceTime, Skype, AppleWatch and whatever the newest methods to 'stay connected', are out there! Seven days a week, I am their stable pony. Since March of 2020, I have worked the day and evening shifts out of the 'Rona Division (gotta keep up with the young people and their language). After all, 'Grandfather likes to be modern in his language'.'Rona Division is not much different than the rest of the SLP workforce, yet it takes this fight against the 'invisible enemy' as its core mission. The core mission of the Division, is to exert the force of the 'Rona mitigations generally recognized as effective, so that the virus becomes part of the noise floor and we clinicians can do our real work. 

Since 'Rona Division was formed back in the spring, we're continually reminded that healthcare never closes. Our education colleagues have realized this as well, with recent events in their work settings. With the dangers of 'Rona ever present, everywhere, all our days, and all our work bags, are filled with personal protective equipment. Hand sanitizer bottles can be found in the bags, in our pockets; riding in cup holders of our cars, and even filling bottles that used to bear motor oil, Coke, bottled water, etc. Ziploc bags are bulging with masks, and with gloves. Since the Spring, I've worn out three face shields. A couple bottles of disinfectant are also stuffed in my portable office. I think we're ready to get out there and do good work, with our armor secured. Then, it's just another day at the office. 

What makes us different than other SLP's? Technique, technique, technique. From the time we arrive at each worksite in which we do our magic, until the final mile to our home base is traced in reverse order to the morning; - keeping the little 'Rona buggers at bay. After all, we're continuing to have close, proximal contact with all persons we serve. There's no teletherapy. There's no apprehension about being close enough,  to interact with your persons served. Following clean technique, so that clean hands manipulate all materials used, - then we do all the normal SLP things we do. We're very clean SLP'S. That cleanliness? Part of the noise floor. The rest is, living in the present. 


It's the noise floor, but it's also a very anxiety - producing part of SLP practice. We're so stressed out, still, by the ominous nature of the disease, that there is an almost dreadful tone we give to each day. You make a mistake in technique, then 'Rona can get you. You get exposed to an infectious person or environment, then 'Rona can get you. You allow yourself to get run down by appointments, commuting, by hours of prep and doc time, - then 'Rona can get you. "There Is A Danger", a post for this blog published 4/5/2020, touches on the dread. I have had to remind my consumers, my colleagues and supervisors, that if you are not old enough to remember the last US polio outbreaks of the 1950's - you may have no memory of real dread. 


The world is, regardless, figuring out what works to mitigate spread of the 'Rona. Cleanliness. Distance and time. Barriers. All part of the noise floor, so 'Rona Division SLP's can live in the present....and help the persons served have a better future. Till therapeutics and vaccines allow us to get the upper hand on this virus, the 'Rona Division keeps us going to deal with real life for our consumers. We keep going through sustained efforts at simple prevention. The rest of the world has also taught us those simple ways.


Checking my texts and emails now. Back to work soon.





